


Expiratory reserve volume (ERV) is the extra air you can still push out after a normal, relaxed breath out. In healthy young adults it is roughly 1.0 to 1.2 liters (1,000 to 1,200 mL) in textbook examples, and often less in women and smaller people. A spirometer measures it directly, and FRC equals ERV plus residual volume.
Breathe out normally, then keep going. That last squeeze, the air you can force out after the relaxed breath has ended, is your expiratory reserve volume. Most of the time, though, you never use it. During exercise, however, your body dips into it to make each breath bigger.
The idea sounds simple, yet it confuses many students because it sits between two other numbers. For example, above it is the tidal volume, the air of a quiet breath. Meanwhile, below it is the residual volume, the air you cannot blow out at all. So ERV is a reserve, not a total.
In short: ERV measures how much room is left to exhale below the resting level of your lungs. For this reason, it links the volumes a spirometer can see with the hidden gas that only special lab tests can find.
The NIH-hosted StatPearls review of pulmonary function tests lists ERV among the volumes that spirometry can measure directly, together with tidal volume, inspiratory reserve volume and vital capacity. By contrast, residual volume, FRC and total lung capacity need gas dilution or body plethysmography.
This guide explains what the number means, how a lab records it, and how to work with it in liters or milliliters. Above all, it is educational only. It does not interpret anyone’s test result, and it does not diagnose anything.
Convert an Expiratory Reserve Volume Between Liters and Milliliters
Lab reports give lung volumes in liters, while many textbooks use milliliters. So type a value below to switch between them. For example, enter 1.1 L to see it as 1,100 mL, or picture it as cups of water.
One milliliter is exactly one cubic centimeter, so some reports write cc instead. If that unit is unfamiliar, see what cc stands for in measurement.
Recommended Study Tools for Lung Volumes
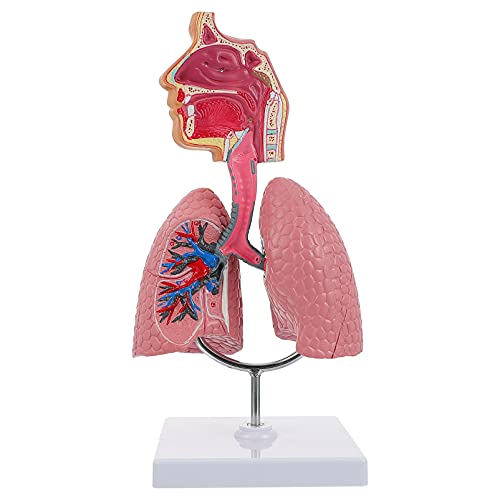
A home gadget will not give you a reliable ERV, so the useful tools here are for learning. First, a solid physiology text explains the spirogram step by step. Next, a physical lung model helps you picture where the reserve air sits. In addition, both work well for nursing, respiratory therapy and biology courses.




As an Amazon Associate, Measuring Expert earns from qualifying purchases.
Key Takeaways
- ERV is the extra air you can exhale after a normal breath out.
- Classic textbook figures put it near 1.1 L for a young adult man and about 0.8 L for a woman.
- Tidal volume (about 0.5 L) sits above it; residual volume sits below it.
- A spirometer can measure ERV because that air actually leaves the mouth.
- FRC = ERV + RV, so ERV is the bridge to residual volume.
- Body size, posture and body weight all shift the value.
- Only a clinician can say what a real test result means.
Where Expiratory Reserve Volume Fits Among Lung Volumes
Physiologists divide the air in the lungs into four basic volumes. Then they add pairs or groups of them to form capacities. Here is the full map, with round teaching values for a healthy young adult man.
| Name | What it describes | Teaching value | Spirometry? |
|---|---|---|---|
| Tidal volume (VT) | Air moved in one quiet breath | about 0.5 L | Yes |
| Inspiratory reserve volume (IRV) | Extra air you can breathe in after a normal breath in | about 3.0 L | Yes |
| Expiratory reserve volume (ERV) | Extra air you can breathe out after a normal breath out | about 1.1 L | Yes |
| Residual volume (RV) | Air left after the hardest breath out | about 1.2 L | No |
| Vital capacity (VC) | IRV + VT + ERV | about 4.6 L | Yes |
| Functional residual capacity (FRC) | ERV + RV, the air left at the end of a quiet breath out | about 2.3 L | No |
| Total lung capacity (TLC) | All four volumes together | about 5.8 L | No |
The numbers add up on purpose: 3.0 + 0.5 + 1.1 = 4.6 L of vital capacity, and 4.6 + 1.2 = 5.8 L in total. However, real people vary a lot, so treat these as a teaching example rather than a target.
Typical Expiratory Reserve Volume Values
Health references often quote an average of about 1,100 mL for men and 800 mL for women. These figures come from classic physiology teaching, so they describe a typical young adult, not a normal range for every person. In practice, labs compare each result with predicted values based on age, sex and height.
| Example group | Liters | Milliliters | About this many US cups |
|---|---|---|---|
| Young adult man (textbook) | 1.1 L | 1,100 mL | 4.65 |
| Young adult woman (textbook) | 0.8 L | 800 mL | 3.38 |
| Common adult teaching range | 1.0 to 1.2 L | 1,000 to 1,200 mL | 4.23 to 5.07 |
The old version of this page listed separate ranges for children and teens. We removed them, because we could not trace them to a reliable source. Of course, children have smaller lungs, so their values are lower, and a pediatric lab uses its own reference equations.
How Spirometry Records the Expiratory Reserve Volume
A spirometer measures air flow at the mouth and adds it up over time. As a result, it can record any volume that actually passes through the mouthpiece. ERV qualifies, because you push that air out during the test.
The test that captures ERV is a slow, relaxed maneuver, not the fast “blow as hard as you can” test. First, you wear a nose clip and breathe quietly through a mouthpiece for a few breaths. This step sets the resting level, the point where a normal breath out ends. Then, at the end of a quiet breath out, you keep exhaling slowly and fully until no more air comes out. The drop below the resting level is the ERV.
Many labs instead record a full slow vital capacity and then split it into parts. In that case, ERV equals vital capacity minus inspiratory capacity (IC), because IC = VT + IRV. Either route gives the same slice of the trace.
How to Find Expiratory Reserve Volume From a Spirogram
Students often get a printed trace or a table and must pull out ERV. Follow these steps with any worked problem.
- Find the resting level: the lowest point of the regular, quiet breaths.
- Find the lowest point of the trace, where the person breathed out as far as possible.
- Subtract the lowest point from the resting level; the gap is ERV.
- If you only have totals, use ERV = VC – IC or ERV = VC – VT – IRV.
- If the problem gives FRC and RV, use ERV = FRC – RV instead.
- Convert liters and milliliters with the converter above, then check that the volumes add up to vital capacity.
For instance, here is a worked example. Suppose vital capacity is 4.6 L, tidal volume is 0.5 L and IRV is 3.0 L. Then ERV = 4.6 – 0.5 – 3.0 = 1.1 L, which is 1,100 mL.
Expiratory Reserve Volume, Residual Volume and FRC
Functional residual capacity is the air in the lungs at the end of a quiet breath out. At that moment, two things are still inside: the air you could push out (ERV) and the air you never can (RV). Therefore:

This identity is how labs find residual volume. A spirometer cannot see RV, so the lab first measures FRC with helium dilution, nitrogen washout or body plethysmography. Next, it subtracts the ERV from spirometry. For example, an FRC of 2.3 L and an ERV of 1.1 L give an RV of 1.2 L. Our guide to how residual volume is measured explains those three methods in detail.
Because RV is calculated from ERV, any error in the ERV maneuver also shifts residual volume. That is also one reason labs repeat the slow test and check that results agree.
What Changes Your Expiratory Reserve Volume
ERV is one of the more changeable lung volumes, since it depends on where the chest settles at rest.
- Body size and sex. Taller people have larger lungs, so their volumes are larger overall.
- Body weight. The StatPearls article on lung capacity explains that obesity lowers ERV, FRC and total lung capacity, because extra weight on the chest and abdomen limits how the lungs expand.
- Posture. Lying down lets the abdominal contents push the diaphragm up, so the resting level falls and less reserve remains.
- Lung and chest conditions. Restrictive and obstructive diseases can both shift the value, which is why only a lab report read by a clinician means anything.
- Effort. A tired or rushed final breath out gives a smaller number.
The old page also claimed that regular exercise “improves ERV”. Exercise has many benefits, but we found no good source showing it reliably raises this particular volume, so we removed that claim.
Do and Don’t When Studying ERV
Do
- Start every problem from the resting level.
- Write FRC = ERV + RV at the top of your notes.
- Check that the volumes add up to vital capacity.
- Keep liters and milliliters separate.
Don’t
- Confuse ERV with residual volume.
- Read ERV from a fast FVC curve alone.
- Treat textbook values as personal targets.
- Interpret a real report without a clinician.
Honest Limits of Expiratory Reserve Volume Testing
ERV is easy to define but sensitive to how the test goes. For one thing, the resting level drifts if the person breathes unevenly before the maneuver. Moreover, the value depends on effort, since a weak final squeeze leaves more air behind. Posture matters as well, so seated and lying results are not interchangeable. Finally, the average figures on this page are teaching values; labs use reference equations instead, and different equations give slightly different predictions. In short, compare a result only with the predicted value from the same lab.
When to Talk to a Doctor
If you have breathing symptoms, or a lung function report you do not understand, talk to your doctor or a pulmonologist. After all, they can explain your numbers alongside your history and other tests. Also, a pulmonary function lab can choose the right maneuvers and reference values for you. The same caution applies to related heart measurements; see how stroke volume is measured for a parallel example.
Expiratory Reserve Volume FAQs
What does expiratory reserve volume measure?
It measures the extra air you can breathe out after a normal, relaxed breath out. It is the reserve below your resting lung level.
What is a normal ERV?
Textbooks often quote about 1,100 mL for a young adult man and about 800 mL for a woman. Labs instead compare results with predicted values for age, sex and height.
Can a spirometer measure ERV?
Yes. ERV is air that leaves the mouth, so a spirometer records it during a slow vital capacity test.
What is the difference between ERV and residual volume?
ERV is the air you can still push out after a normal breath out. Residual volume is the air that stays in the lungs even after the hardest breath out.
How do ERV and FRC relate?
FRC equals ERV plus residual volume. So if you know FRC and ERV, you can calculate residual volume as FRC minus ERV.
How do you calculate ERV from vital capacity?
Subtract tidal volume and inspiratory reserve volume from vital capacity. For example, 4.6 – 0.5 – 3.0 = 1.1 L.
Is ERV the same as tidal volume?
No. Tidal volume is the air of one quiet breath, about 0.5 L. ERV is the extra air below the end of that quiet breath.
Why does ERV drop when lying down?
Lying down lets the abdomen push the diaphragm upward. As a result, the lungs rest at a lower level and less reserve air remains.
Does body weight affect ERV?
Yes. Extra weight on the chest and abdomen limits lung expansion, so obesity tends to lower ERV and FRC.
Is ERV measured in liters or milliliters?
Lab reports usually use liters, while textbooks often use milliliters. One liter equals 1,000 mL, so 1.1 L is 1,100 mL.
The Bottom Line
Expiratory reserve volume is the extra air you can push out after a relaxed breath out, roughly 1.0 to 1.2 L in textbook adult examples. A spirometer records it directly, and it links the movable volumes with the hidden ones through FRC = ERV + RV.
So for exams, find the resting level first and remember that capacities are sums. For real results, however, rely on a pulmonary function lab and your doctor rather than average figures.